


12% Medicare Advantage denies one in eight admissions
Two-thirds of facilities face MA denials weekly or daily. Two-thirds also report plans ending coverage against medical advice.

Healthcare · UK & Europe
Your team is not wrong about the denials. They just do not have four hours per appeal to prove it.
of denied skilled nursing admission requests are ever appealed, despite a 95% overturn rate on those that are.
In the UK and Europe
Platforms in this market
Rules that apply here
We read the rule before the call. It is the cheapest way to prove we did the work.
What is happening
Two-thirds of facilities face MA denials weekly or daily. Two-thirds also report plans ending coverage against medical advice.

The evidence sits in nursing narrative, therapy notes and the MDS. Your billing platform submits claims. It cannot argue one.

Speech components carry a 38% error rate, non-therapy ancillary 31%, nursing 27%. Therapy, which is counted in minutes rather than described in words, sits at 2%.

Top performers answer in 15 to 30 minutes. Responding inside the first hour doubles conversion. Around 30% of referrals are lost to slow response alone.
Your EHR reports per facility. Leadership rebuilds the portfolio view in a spreadsheet every Monday, by which point the numbers are three days old.
However hard, whatever it is
We wrote this about appeals nobody has hours for. If yours is coding, census or a survey finding, the method does not change.
 01
Days where the work happens, not a workshop in a meeting room. We watch the job get done and write down the shortcuts nobody wrote down.
 02
Your data, your rules, your vendors and their documentation, and the published research on your sector. We report what is actually in there.
 03
Not which tool fixes this. What is actually causing it, taken apart until we reach the piece that cannot be divided further.
 04
Weeks, not quarters. By this point we are not guessing what to build, and guessing is the thing that makes projects long.
Where we sit
What you get
Built new for you — none of this exists in your stack today
What you already run — unchanged, and still yours
If the chart or the remittance holds it, we can reach it. FHIR where it exists, a scanned denial letter, a fixed-width payer file. We have built against all three.
 No API
 No documentation
 A terminal from 1994
 It arrives as paper
 The vendor said no
 It reports nothing
Not a list of limits. Name yours on the call.
And once we can reach it, a model can read it. Most of the value here is in the sources nobody ever structured — the note, the letter, the screen.
Intelligence, plumbed in
We build retrieval over the chart, one coding vocabulary in the layer, and an eval set of assessments already audited.
How we make AI survive real data Connectors
 A semantic layer
 Evals you can check
What changes
 Denials worked
Denials surfaced, aged, assigned and packaged with the clinical evidence already assembled. Deadlines tracked through redetermination and reconsideration.
 Revenue recovered
We can work this on contingency. A share of what is recovered, and nothing if nothing is recovered.
 Capture rate
The qualifying condition is usually already in the nursing note. It simply never reached the assessment. We reconcile the two.
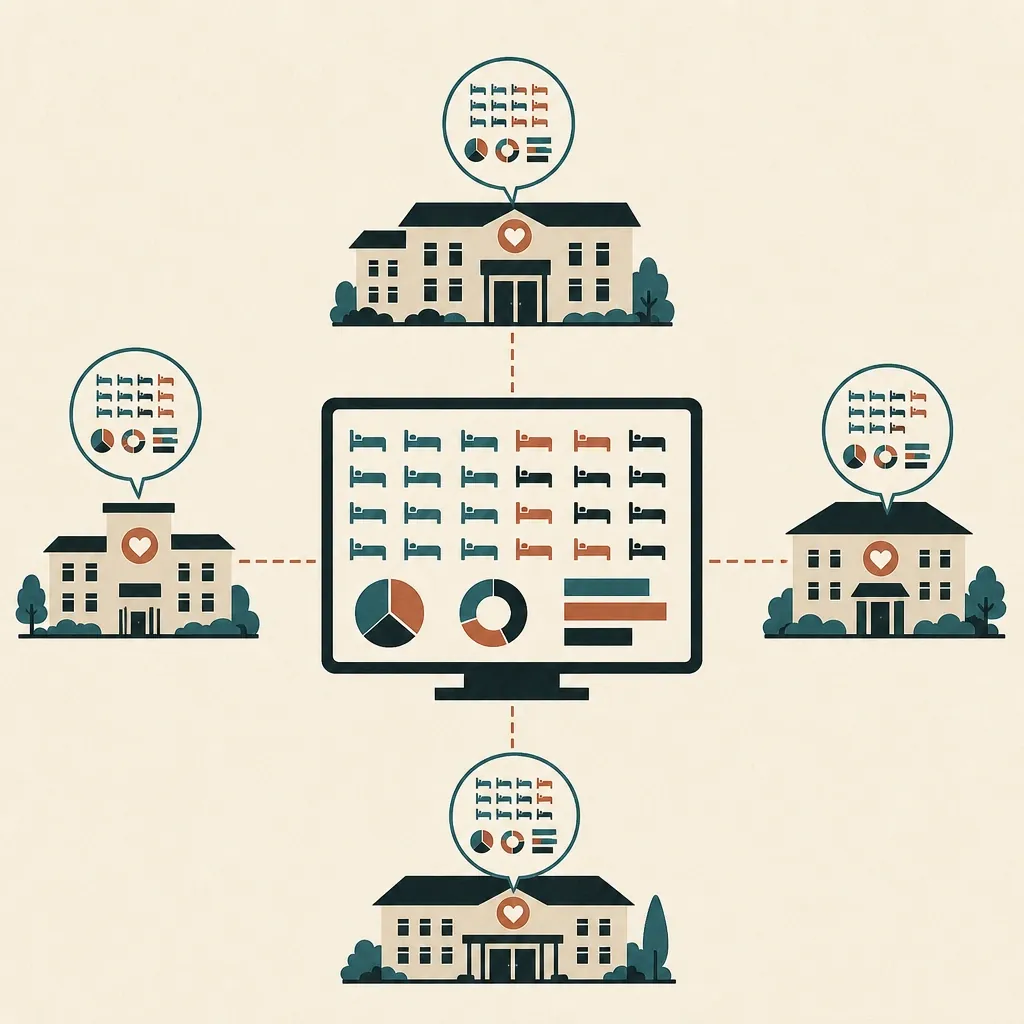 One view
Occupancy, payer mix, admissions and discharges reconciled to what each facility reports. No Monday rebuild.
Who this is for
 Chief Operating Officer
 VP of Revenue Cycle
 Director of Clinical Services
 Regional Director of Operations
 CFO
Straight answers

Yes. We have built production integrations against PointClickCare and eClinicalWorks, including the parts that are not in the documentation. In March 2025 a Fourth Circuit ruling confirmed that blocking third-party API access counts as information blocking under the Cures Act. That puts you on stronger ground when you ask for your own data.

Two ways. A fixed-price build starting at $25,000, or contingency — a share of what we actually recover, and nothing if we recover nothing. Most operators start with contingency because it removes the risk of finding out.

A few weeks. We take read-only access. We come back with what is really in your system, the three questions you cannot answer today, and a dollar figure on the biggest leak. That is yours whether or not we carry on.

Yes. We sign a Business Associate Agreement before any access. PHI is encrypted at rest and in transit, access is logged per record, and infrastructure sits in US regions.

Yes. That is retrieval over the chart, scored against assessments already audited. The coder decides; the system only points.
For skilled nursing that means CQC fundamental standards, UK GDPR, the Care Act 2014 and local authority funding rules. We read the rule before the call, so the first meeting is about your operation rather than about us catching up.
What you already run stays where it is. Around it we build software, hardware and the process itself. Here that means an appeal pack built from the chart in minutes, not days.
See everything we build Software
 Hardware
 Ways of working
 Whole ventures
Honest about the numbers
We have not localised it, because a number nobody can check is worth less than a real one plus this sentence. The pattern travels. The size of it in your market is a question for the call.
Same industry, other markets